

Direct answer: A conceptual framework for a public health thesis is a diagram, with a short explanation, that shows the variables or program components in your study and how you expect them to relate. For public health, three structures cover most theses: the social-ecological model, which maps influences on a health outcome from the individual to society; a program logic model, which links inputs, activities, outputs and outcomes; and a theory-based model such as the Health Belief Model, which turns a behavior theory into named, measurable constructs. Choose the structure that matches your question, draw it with labeled arrows, and make every box something you will measure.
The difference between a theoretical framework and a conceptual framework is explained in the guide to theoretical versus conceptual frameworks. This article is the public health version: three worked examples you can adapt, how to draw them, and the mistakes that committees flag in MPH and doctoral public health proposals.
What the framework has to do
A good framework does four jobs. It names the main variables in your research questions. It shows the direction of the relationships you hypothesize. It cites the theory or model that justifies those relationships. And it shows what you will measure, so that your instruments and analysis in chapter three follow directly from the picture. If a box in your diagram has no measure, or a measure in chapter three has no box, the framework is not finished.
Option 1: the social-ecological model
The social-ecological approach in health promotion builds on McLeroy and colleagues’ ecological perspective on health promotion programs (1988, Health Education Quarterly, 15(4), 351-377). The model holds that health behavior is shaped by several levels of influence. The CDC uses a four-level version in its violence prevention work, with the individual, relationship, community and societal levels, and notes that the overlapping rings show how factors at one level influence factors at another and that prevention is more likely to be sustained when it acts on several levels at once. Other applications add an organizational or policy level, so say which version you adopt and cite it.
When to choose it. Your question concerns a health outcome with causes at several levels, such as adolescent vaping, childhood obesity, or maternal health disparities, and you want to show why a single-level explanation is not enough.
Illustrative example (adolescent vaping). The diagram has four nested rings. Individual: attitudes toward vaping, nicotine dependence, self-efficacy to refuse. Relationship: friends who vape, parental monitoring, sibling use. Community: availability of retailers near schools, school tobacco policy enforcement. Societal: state flavor restrictions, advertising exposure. Arrows from each ring point to the outcome, current vaping in the past 30 days. Your methods chapter then names one measure per box, for example a validated attitude scale, a count of friends who vape, a school-level policy score and a state-level policy indicator.
How to keep it feasible. A thesis cannot measure everything. Draw all four levels if you want the reader to see the whole system, but shade the boxes you will measure and mark the rest as context, and attach a named measure, a scoring rule and a data source to each shaded box.
Option 2: a program logic model
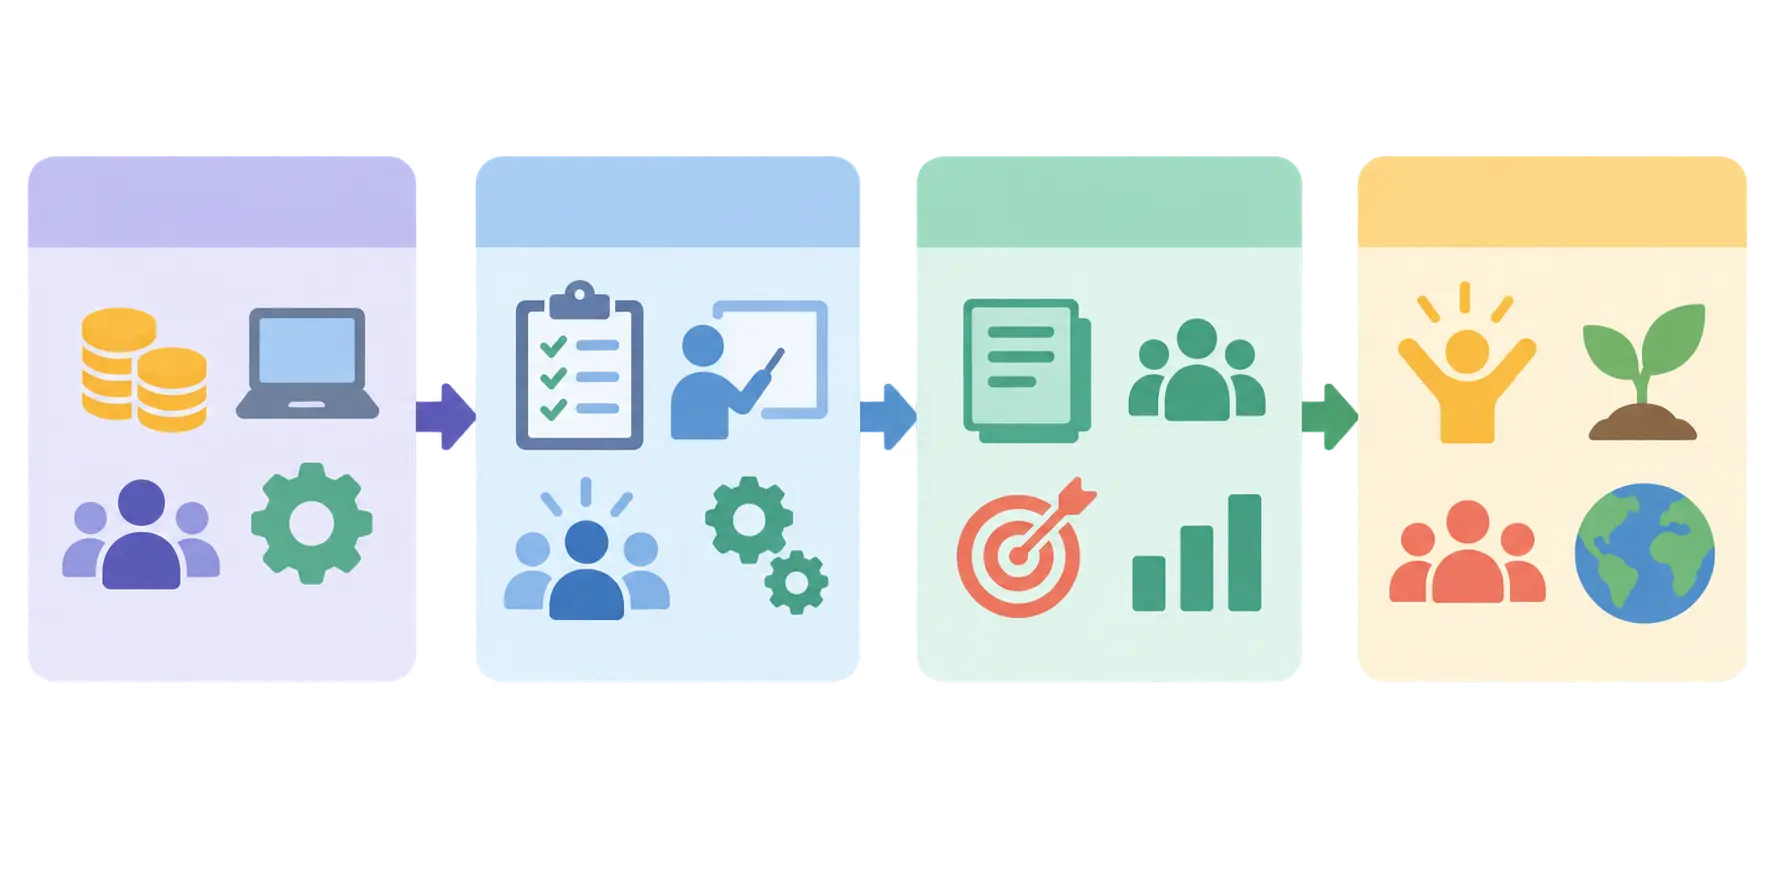
A logic model suits capstones and evaluations of an intervention. In CDC’s program evaluation resources, a logic model is a graphic road map of the relationships among a program’s resources, activities, outputs, outcomes and impact, depicting the relationship between the program’s activities and its intended effects. In practice most theses use four columns: inputs (the resources needed), activities (what the program does with them), outputs (the direct products of activities) and outcomes (the intended effects, often split into short-term, intermediate and long-term), read as a chain of if-then assumptions.
When to choose it. You are evaluating or designing a program, and your questions are about whether it was delivered as planned and whether it achieved its intended effects.
Illustrative example (a community walking program). Inputs: a grant, two health educators, a partnership with a parks department. Activities: weekly guided walks, text-message reminders, a tracking app. Outputs: number of walks held, number of participants attending at least four times. Short-term outcomes: increased self-reported weekly walking minutes. Intermediate outcomes: sustained walking at six months. Long-term outcomes: improved fitness and lower blood pressure in the participant group. Each outcome box gets an indicator, a data source and a time point, and the arrows between the boxes are your if-then assumptions. Write those assumptions in a sentence under the diagram, for example “if participants attend at least four walks, then their weekly walking minutes will increase”.
Option 3: a theory-based behavior model
If your question is about why people do or do not adopt a health behavior, turn a behavior theory into a conceptual framework by listing its constructs as variables. The Health Belief Model is a common choice: it organizes beliefs about susceptibility, severity, benefits, barriers, cues to action and self-efficacy as predictors of a health action such as vaccination or screening. Cite the original theory source from your own literature review, and define each construct operationally, for example perceived barriers as the mean score on a named barriers scale.
Illustrative example (screening uptake). Boxes for perceived susceptibility, perceived severity, perceived benefits, perceived barriers and self-efficacy each point to a box labeled “completed screening in the past 12 months”, while demographic variables such as age and insurance status enter as controls. The analysis in chapter three is then a logistic regression with those variables, and the framework predicts a direction for each coefficient.
Mediators, moderators and controls in the diagram
Many public health questions are not a single arrow from exposure to outcome. A mediator sits on the path between them, so the arrow runs from exposure to mediator to outcome; in the walking program, weekly attendance might mediate the effect of text reminders on walking minutes. A moderator changes the strength of a relationship, and is drawn as an arrow pointing at another arrow; neighborhood walkability might moderate the effect of the program. Controls are variables you adjust for but do not interpret, such as age and income, and they are usually drawn at the edge of the diagram. If you include any of these, name the statistical approach that will test them in chapter three, so the diagram and the analysis plan agree.
How to draw the diagram
- List your variables first. Write the outcome, the main exposures or program components, mediators or moderators, and controls in a table with the measure for each.
- Place the outcome on the right and the main influences on the left. Put controls at the top or bottom so they do not crowd the main path.
- Use arrows only for relationships you hypothesize. Label them with the sign you expect, plus or minus, or number them to match your hypotheses.
- Use different shapes for different roles. For example rectangles for measured variables, ovals for latent constructs, and dashed boxes for context you will not measure.
- Add a legend and a caption. Say what the arrows and shapes mean and cite the source model.
- Write a one-paragraph walk-through. Explain the diagram in words, from left to right, citing the literature for each key link.
A free tool such as a drawing app or a slide program is enough; examiners care about clarity and accuracy, not artistry.
Writing the walk-through paragraph
The paragraph under the figure is where examiners check your reasoning. An illustrative version for the screening example: “Figure 1 shows the conceptual framework. Following the Health Belief Model, perceived susceptibility, severity, benefits and barriers, and self-efficacy are hypothesized to predict screening uptake. Perceived benefits and self-efficacy are expected to be positively associated with uptake, and perceived barriers negatively associated. Age and insurance status are included as controls.” Each sentence maps to something in the diagram, names the source model and states a direction. If you cannot write a sentence for an arrow, remove the arrow or find the literature that supports it.
Linking the framework to the rest of the thesis
The framework should reappear in every chapter. In chapter one it motivates the problem. In chapter two it organizes the literature review, with a section for each box or link. In chapter three it dictates your instruments, sample and analysis plan. In the results it structures the tables, and in the discussion you return to it to say which links were supported. For a thesis built on a systematic review, the framework often becomes the coding scheme for extracted data, as described in the guide to a systematic review as a public health thesis. For how to define the population your framework applies to, see the guide to population, sample and sampling for a public health thesis.
Mistakes that committees flag
- A diagram that lists theories but shows no relationships among variables.
- Boxes that are not measured anywhere in the methods chapter.
- Arrows that imply causation your design cannot support, for example in a cross-sectional survey.
- Using a model’s name without citing it or explaining why it fits the question.
- Copying a published diagram without adapting it to your variables.
- A framework introduced in chapter one and never mentioned again.
Where this fits in the wider thesis
The framework is one part of the proposal and the first chapters. For the full chapter structure of a public health dissertation, see the guide to how to write a public health dissertation.
Where Tesify fits
When your variables and model are chosen, Tesify’s thesis workspace helps you structure the framework section and the chapters that depend on it; 9,000+ students have written 15,000+ chapters with Tesify. Every word stays 100% written by you, and Tesify cannot choose the theory that fits your question or confirm that a model is cited correctly.
Frequently asked questions
What is the difference between a theoretical and a conceptual framework?
A theoretical framework is the established theory or model you build on, while a conceptual framework is your own diagram of the variables and relationships in your study, justified by that theory.
Which model should an MPH thesis use?
Use the social-ecological model for multilevel influences, a logic model for program evaluation, and a behavior theory such as the Health Belief Model for individual decision-making; let your question decide.
Can I combine two models?
Yes, if you explain how they fit together, for example using a logic model for the program and a behavior theory to explain the mechanism between activities and outcomes.
How many variables should the diagram contain?
As many as you will measure and no more; a diagram with a dozen unmeasured boxes invites questions you cannot answer.
Do I need a figure, or is a written description enough?
Most committees expect a figure with a written explanation. A description alone is hard to check against your methods.
Should arrows show causation?
Only if your design supports it. For cross-sectional data, say the arrows show hypothesized associations.
Where in the thesis does the framework go?
Usually at the end of chapter one or in chapter two, and it is revisited in the methods and discussion chapters.
Can I adapt a published framework?
Yes, with citation and a clear statement of what you changed and why.
Write your thesis with AI
Structure, draft, cite, and format your thesis faster with Tesify’s AI writing tools, automatic bibliography, and plagiarism checker. Free to start, no credit card required.






Leave a Reply